Thomas Levy, MD: Iron Overload, Oxidative Stress, Liver, Brain & Gut Health
Iron is essential for oxygen transport, energy production and normal cellular function—but excess iron can become a powerful source of oxidative stress. In his Riordan Clinic lecture, Iron and Gluten: The Toxic Tandem, Thomas E. Levy, MD, JD focuses particularly on added iron in fortified foods, intestinal inflammation and the danger of assuming that more iron is always beneficial. His central message is practical: before supplementing iron, determine whether you actually need it.

Thomas Levy, MD: Iron Overload, Oxidative Stress, Liver, Brain & Gut Health
Iron is essential for oxygen transport, energy production and normal cellular function—but excess iron can become a powerful source of oxidative stress. In his Riordan Clinic lecture, Iron and Gluten: The Toxic Tandem, Thomas E. Levy, MD, JD focuses particularly on added iron in fortified foods, intestinal inflammation and the danger of assuming that more iron is always beneficial. His central message is practical: before supplementing iron, determine whether you actually need it.
Watch Thomas Levy, MD: Iron and Gluten, The Toxic Tandem
In this Riordan Clinic presentation, Levy examines iron exposure from supplements and fortified foods and develops his hypothesis that chronic intestinal exposure to added iron may contribute to oxidative stress, inflammation and increased intestinal permeability.
Why Can Too Much Iron Be Harmful?
Iron is essential for hemoglobin, oxygen transport, mitochondrial energy production, DNA synthesis and many enzyme systems.
But iron is also a highly reactive transition metal. Iron can change oxidation state and participate in reactions that convert hydrogen peroxide into extremely reactive hydroxyl radicals. This chemistry is commonly known as the Fenton reaction.
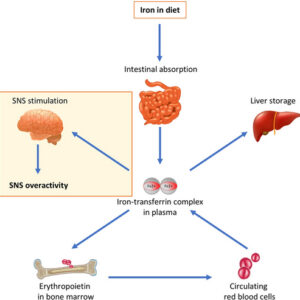
Normally, proteins such as transferrin and ferritin keep iron tightly controlled. When iron exposure or accumulation exceeds the body's ability to safely transport and store it, iron's chemical reactivity becomes increasingly important.
Levy's Main Concern: Added Iron in Fortified Foods
One of the most distinctive parts of Levy's presentation concerns the iron deliberately added to processed foods.
He draws an important distinction between naturally occurring dietary iron and forms of iron introduced during food enrichment and fortification.
Common sources of added iron include:
- Breakfast cereals
- Enriched wheat flour
- Breads and baked goods
- Pasta
- Rice products
- Meal-replacement products
- Infant cereals and formulas
- Multivitamins and nutritional supplements
What Does “Reduced Iron” Mean on a Food Label?
Levy devotes considerable attention to products listing reduced iron as an ingredient.
In the lecture, he demonstrates that elemental iron added to some fortified foods can be physically separated with a magnet. He contrasts this with ionic iron preparations such as ferrous sulfate.
When reading food or supplement labels, iron may appear as:
- Reduced iron
- Elemental iron
- Ferrous sulfate
- Ferrous fumarate
- Ferrous gluconate
- Iron-fortified or enriched flour
Iron Overload and Oxidative Stress
Oxidative stress is the biochemical thread connecting many of Levy's concerns about excess iron.
Lipid Peroxidation
Iron-generated free radicals can attack fatty acids within cellular and mitochondrial membranes and initiate lipid peroxidation.
Oxidative DNA Damage
Reactive oxygen species can alter DNA bases. Markers such as 8-OHdG can help evaluate oxidative DNA damage.
Cellular Energy
Mitochondria are particularly susceptible to oxidative injury because they continuously generate and utilize energy through redox reactions.
Iron and the Liver
The liver plays a central role in regulating and storing iron. It produces hepcidin, one of the primary hormones controlling intestinal iron absorption and release of stored iron into circulation.
At the same time, the liver is one of the major organs injured by significant iron accumulation.
- Excess iron can increase hepatic oxidative stress
- Iron can promote lipid peroxidation
- Oxidative signaling can contribute to inflammation
- Longstanding overload can contribute to fibrosis
- Severe iron overload can eventually produce cirrhosis
- Advanced iron-related liver disease increases hepatocellular carcinoma risk
How Excess Iron Can Impair Methylation
The relationship between excess iron and methylation is more specific than simply saying that both involve the liver.
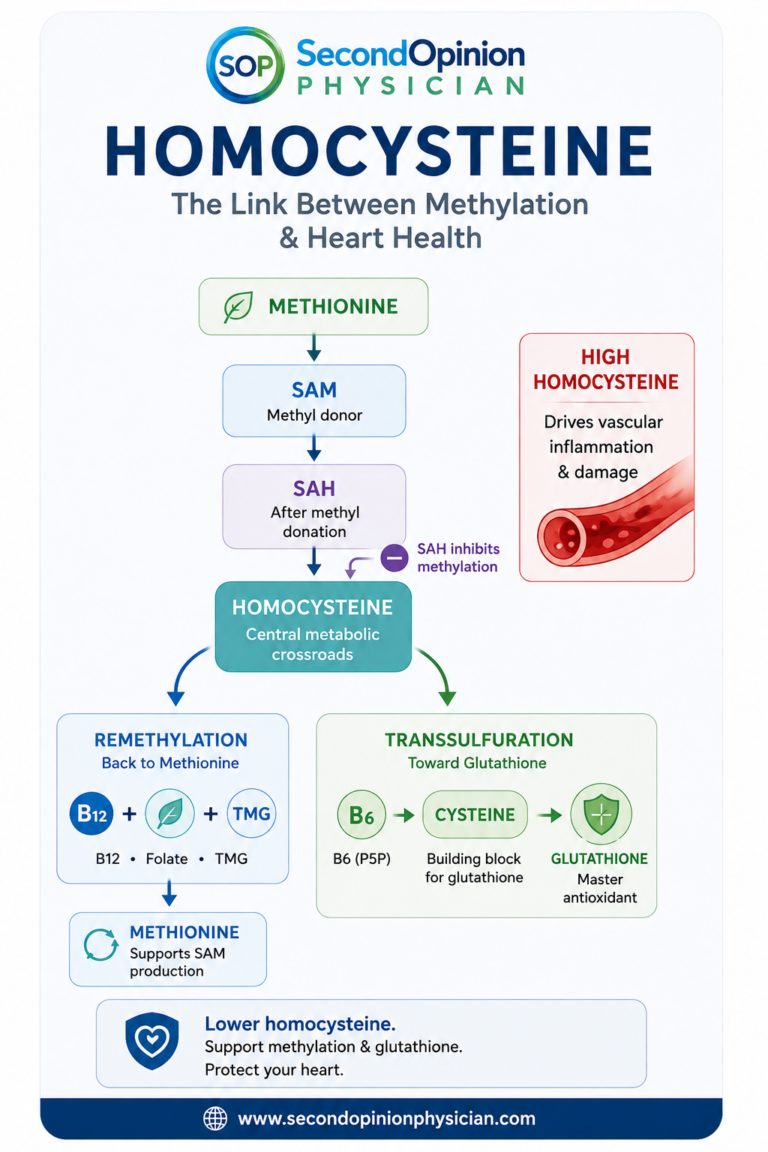
Excess reactive iron increases oxidative stress through Fenton chemistry. The liver is particularly important because it is both a major site of iron storage and the principal organ responsible for much of the body's methionine metabolism and production of SAM, or S-adenosylmethionine.
SAM is the major methyl donor used for DNA methylation, neurotransmitter metabolism, phospholipid synthesis, protein methylation and hundreds of other biochemical reactions.
Oxidative Stress Can Reduce SAM Production
The first major step in the methylation cycle is the conversion of methionine into SAM by the enzyme methionine adenosyltransferase, or MAT.
The adult liver predominantly uses the MAT1A form of this enzyme. Hepatic oxidative and redox stress can interfere with MAT1A activity or expression and therefore reduce efficient conversion of methionine into SAM.
Potential consequence: less SAM means less available methyl-donor capacity for methyltransferase reactions.
Iron Can Create a SAM–Glutathione Feedback Problem
SAM does more than donate methyl groups. Methionine metabolism is also connected to the transsulfuration pathway that ultimately supports production of glutathione, one of the liver's principal intracellular antioxidants.
This creates a potentially important feedback loop: iron increases oxidative demand at the same time that hepatic injury may weaken SAM metabolism and antioxidant resilience.
Potential feedback loop: excess iron → greater oxidative stress → impaired SAM metabolism → less antioxidant resilience → still greater oxidative stress.
SAH Can Directly Inhibit Methylation
After SAM donates its methyl group, it becomes SAH, or S-adenosylhomocysteine.
SAH is a potent inhibitor of many methyltransferase enzymes. For methylation to continue efficiently, SAH must be cleared through SAH hydrolase toward homocysteine and adenosine.
Iron overload has not been shown to create one predictable SAM/SAH pattern in every person. The important point is that iron-induced liver and mitochondrial stress can disturb the metabolic environment in which SAM is produced, SAH is processed and glutathione is regenerated.
Oxidative Stress Can Alter Epigenetic Methylation
The effect can extend beyond circulating nutrient markers.
Altered hepatic SAM availability and chronic oxidative stress can influence DNA and histone methylation, potentially changing gene expression.
Abnormal methylation patterns have been observed in chronic liver injury and iron-overload states, although this does not mean every person with elevated iron develops the same epigenetic pattern.
Clinical interpretation: iron overload should not automatically be labeled an “undermethylation disorder,” but excessive iron can create conditions capable of impairing normal methylation biology.
Why SAM and SAH Testing May Be Useful
If iron overload occurs together with oxidative stress, abnormal liver markers, fatigue or other metabolic problems, measuring methylation directly may provide more useful information than assuming the pathway is normal.- SAM
- SAH
- SAM:SAH ratio
- Methionine
- Homocysteine
- Related transsulfuration and glutathione pathways
Iron and the Brain
Iron is necessary for normal brain function. It participates in mitochondrial metabolism, myelin formation and neurotransmitter synthesis.
However, the brain is particularly sensitive to oxidative injury because it consumes large amounts of oxygen and contains abundant oxidation-sensitive lipids.
Abnormal iron accumulation has been studied in:
- Parkinson's disease
- Alzheimer's disease
- Huntington's disease
- Amyotrophic lateral sclerosis
- Other neurodegenerative disorders
Iron accumulation does not establish that iron is the sole cause of these disorders. Rather, abnormal iron handling and iron-mediated oxidative stress are increasingly recognized components of neurodegenerative biology.
Iron, the Gut and Intestinal Oxidative Stress
The gastrointestinal tract is one of the most important themes in Levy's lecture.
The intestine is where dietary iron enters the body, but unabsorbed iron also remains in direct contact with intestinal cells and microorganisms.
Local Oxidative Stress
Excess luminal iron may participate in oxidative reactions affecting intestinal lipids, proteins and epithelial cells.
Microbial Iron
Many bacteria require iron for growth and have sophisticated systems for extracting it from their environment and from host iron-binding proteins.
Levy's Iron and “Leaky Gut” Hypothesis
Levy goes beyond systemic iron overload and proposes that repeated intestinal exposure to added iron may produce chronic inflammation of the intestinal lining.
This forms the basis of his “iron and gluten toxic tandem” hypothesis. Levy argues that increased permeability may allow incompletely digested proteins and other molecules to interact more extensively with the immune system.
Could Going Gluten-Free Also Reduce Iron Exposure?
Levy makes an interesting observation in the lecture: many people who eliminate conventional wheat products simultaneously reduce their exposure to enriched flour.
Many organic and gluten-free foods are not iron-fortified to the same degree as conventional enriched grain products.
Iron and the Gut Microbiome
The interaction between iron and intestinal microorganisms is complex.
Many pathogenic microorganisms require iron. Some produce specialized molecules called siderophores that help them acquire iron from their environment or from host proteins.
Research on oral iron supplementation has shown mixed microbiome effects. In some circumstances, additional intestinal iron has been associated with:
- Changes in bacterial composition
- Increased growth opportunities for iron-dependent organisms
- Greater local oxidative stress
- Changes in intestinal inflammatory signaling
Iron, Infection and the Immune System
Iron availability is tightly regulated during infection.
The body can deliberately reduce circulating iron and sequester it within storage proteins as part of the immune response. This helps limit the availability of iron to microorganisms.
Iron and Copper Overload: Two Redox-Active Metals
Levy repeatedly discusses iron together with copper.
Both are essential transition metals. Both can change oxidation state. And both can promote oxidative reactions when present in excess or when poorly regulated.
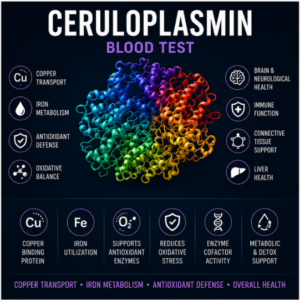
Their physiology also intersects. The copper-containing protein ceruloplasmin has ferroxidase activity that helps convert iron into a form that can bind transferrin for transport.
Ferritin and Transferrin
Iron requires controlled storage and transport to prevent inappropriate participation in oxidative chemistry.
Copper and Ceruloplasmin
Copper-containing proteins participate in normal iron handling. Poor regulation of either iron or copper can add to overall oxidative burden.
Ferritin: Levy's View Versus Standard Interpretation
Levy places substantial emphasis on ferritin because ferritin reflects stored iron.
In his lecture, he argues that conventional laboratory reference ranges tolerate considerably greater iron storage than he believes is biologically optimal.
Ferritin is also an acute-phase reactant and can rise in many conditions:
- True iron overload
- Inflammation
- Fatty liver disease
- Alcohol-related liver injury
- Infection
- Metabolic dysfunction
- Other chronic disease
What Tests Help Identify Iron Overload?
Ferritin is important, but it should generally be interpreted as part of a complete iron pattern.
| Laboratory Test | What It Helps Evaluate |
|---|---|
| Ferritin | Stored iron. Low ferritin strongly supports iron deficiency. High ferritin requires interpretation because inflammation and liver disease can also elevate it. |
| Serum Iron | Measures circulating iron at the time of testing. It should not usually be interpreted alone. |
| TIBC / Transferrin | Measures or estimates the blood's capacity to bind and transport iron. |
| Transferrin Saturation | Shows the percentage of transferrin occupied by iron and is particularly useful when evaluating possible iron overload. |
| CBC | Evaluates hemoglobin, hematocrit, MCV and other blood-cell findings that help distinguish iron deficiency from other forms of anemia. |
| CMP / Liver Enzymes | Provides information about hepatic and metabolic function that can help explain an abnormal ferritin. |
Transferrin Saturation and Hemochromatosis
When ferritin and transferrin saturation are persistently elevated, hereditary hemochromatosis becomes an important consideration.
Hemochromatosis is an inherited disorder in which regulation of intestinal iron absorption is impaired, allowing progressive accumulation of iron in tissues.
Depending on the laboratory pattern and clinical history, further evaluation may include:
- Repeat iron studies
- HFE genetic testing
- Liver assessment
- Evaluation of family history
- MRI-based measurement of hepatic iron in selected cases
Why You Should Not Automatically Take Iron for Fatigue
Fatigue is one of the most common reasons people start iron supplements, but fatigue is extremely nonspecific.
Other causes can include:
- Thyroid dysfunction
- Vitamin B12 deficiency
- Inflammation
- Sleep disorders
- Hormonal abnormalities
- Chronic infection
- Kidney disease
- Liver disease
- Mitochondrial dysfunction
- Methylation abnormalities
- Anemia unrelated to iron deficiency
Measure first. Supplement second.
Iron replacement is appropriate when genuine iron deficiency exists. Iron is much less appropriate as a nonspecific treatment for fatigue when iron status has never been measured.Even Levy Supports Iron When True Deficiency Exists
Levy's presentation is strongly critical of unnecessary iron exposure, but his actual message is more nuanced than simply “never use iron.”
Near the conclusion of the lecture, Levy specifically acknowledges that when true iron-deficiency anemia is present, iron replacement may be necessary.
Documented Iron Deficiency
Iron supplementation can be appropriate when laboratory findings establish a genuine need and the underlying reason for the deficiency is investigated.
Routine Supplementation
Continuing to add iron after iron stores have become adequate provides little rationale and may unnecessarily increase oxidative and gastrointestinal exposure.
Oxidative Stress Testing When Iron Is Elevated
If the concern is that excessive iron may increase oxidative stress, it can be useful to determine whether oxidative damage is actually measurable.
8-OHdG
8-hydroxy-2'-deoxyguanosine is a commonly used marker of oxidative DNA damage.
Lipid Peroxides
Lipid-peroxidation markers can help evaluate oxidative damage affecting fatty acids and cellular or mitochondrial membranes.
Hair Mineral Analysis and Iron Overload
Hair mineral and toxic-element analysis can provide information about broader patterns of mineral and toxic-metal exposure.
Depending on the panel, this can include:
- Copper
- Zinc
- Mercury
- Lead
- Arsenic
- Cadmium
- Other essential and toxic elements
A Broader Iron and Oxidative Stress Evaluation
Iron + TIBC + Ferritin
Helps distinguish iron deficiency, increased storage, inflammatory sequestration and patterns suggesting possible iron overload.
Iron Testing8-OHdG & Lipid Peroxides
Helps determine whether oxidative damage accompanies an iron, copper, inflammatory or mitochondrial abnormality.
Oxidative Stress TestingCopper, Zinc & Ceruloplasmin
Evaluates copper metabolism, zinc balance and another major redox-active metal system.
Copper Overload PanelSAM, SAH & Homocysteine
Evaluates methylation capacity, SAH inhibition, methionine and homocysteine metabolism and related antioxidant pathways.
Methylation PanelHair & Toxic Elements
Provides a broader view of essential mineral patterns and toxic-metal exposure.
Hair AnalysisCBC & Metabolic Testing
Provides context regarding anemia, liver function, kidney function and other metabolic findings affecting interpretation of ferritin.
View Lab TestingWhat If Iron Overload Is Confirmed?
Treatment depends on the reason iron is elevated.
For hereditary hemochromatosis and many forms of clinically important iron overload, therapeutic phlebotomy is the established method for reducing total-body iron when medically appropriate.
Other forms of secondary iron overload may require specialized treatment, including management of the underlying disorder or prescription iron-chelating medications.
How Iron Fits With Dr. Levy's Vitamin C and Redox Work
Iron provides an important connection to Levy's broader work on vitamin C, glutathione, infection and oxidative stress.
Much of Levy's clinical framework revolves around redox balance: identifying what continually produces oxidative pressure and whether antioxidant systems can adequately restore damaged molecules.
Potential contributors include:
- Excess iron
- Excess or poorly regulated copper
- Chronic inflammation
- Infection
- Toxic exposures
- Mitochondrial dysfunction
- Impaired glutathione metabolism
- Methylation abnormalities
Our Approach: Test Before Supplementing Iron
The most useful practical lesson from Levy's presentation is not that iron is inherently harmful. Iron is necessary for life.
The important principle is that an essential nutrient should not automatically be assumed to provide greater benefit at progressively higher doses.
Before routinely supplementing iron, especially for long periods, consider:
- Is iron actually deficient?
- What is the ferritin?
- What is the transferrin saturation?
- Are serum iron and TIBC consistent with deficiency or excess?
- Is inflammation changing iron distribution?
- Could fatty liver or liver disease be increasing ferritin?
- Is hereditary hemochromatosis possible?
- Is oxidative stress measurably elevated?
- Are copper and zinc also abnormal?
- Are SAM, SAH or glutathione pathways under stress?
- Could gastrointestinal inflammation be affecting iron handling?
Test → Identify the Pattern → Find the Cause → Then Treat
Iron replacement can be extremely important when deficiency is present. But indefinite iron supplementation without evidence of deficiency is very different from correcting documented iron deficiency.Frequently Asked Questions About Iron Overload
What does Thomas Levy say about iron overload?
Thomas Levy emphasizes that iron is essential in appropriate amounts but can become a powerful promoter of oxidative stress when excessive. His lecture focuses particularly on routine iron supplementation and iron added to fortified and enriched foods.
Why does Dr. Levy criticize iron-fortified foods?
Levy argues that widespread iron fortification exposes many people who are already iron-replete to additional iron. He focuses especially on elemental or reduced iron added to enriched grain products and its potential effects on intestinal and systemic oxidative stress.
What is reduced iron in cereal?
Reduced iron is a form of elemental iron used to fortify some foods. In his lecture, Levy demonstrates that magnetic elemental iron can be recovered from certain fortified cereal products and distinguishes this from ionic iron salts such as ferrous sulfate.
Can too much iron cause oxidative stress?
Yes. Reactive iron can participate in Fenton chemistry, generating hydroxyl radicals capable of damaging lipids, proteins, DNA and mitochondria.
How can excess iron impair methylation?
Excess reactive iron can increase hepatic oxidative and mitochondrial stress. This may interfere with methionine adenosyltransferase activity and reduce efficient production of SAM, the body's major methyl donor. Oxidative liver stress can also affect glutathione metabolism and the broader SAM, SAH and homocysteine pathways.
Does high ferritin mean iron overload?
No. Ferritin reflects stored iron but is also an acute-phase reactant. Inflammation, infection, fatty liver, alcohol-related liver injury and other conditions can increase ferritin. Ferritin should be interpreted with transferrin saturation and other iron studies.
What blood tests are used to check for iron overload?
Initial testing commonly includes ferritin, serum iron, TIBC or transferrin and calculated transferrin saturation. CBC and liver testing provide useful additional context.
Can iron overload affect the liver?
Yes. Significant iron accumulation can increase liver oxidative stress, lipid peroxidation and inflammation. Longstanding severe iron overload can contribute to fibrosis, cirrhosis and increased risk of hepatocellular carcinoma.
What is the relationship between iron and copper overload?
Iron and copper are both essential redox-active metals whose metabolism intersects. Ceruloplasmin, a copper-containing protein, participates in normal iron transport. Excess iron and excess copper are different abnormalities, but either can contribute to oxidative burden.
Can excess iron affect the gut?
Excess intestinal iron can influence oxidative chemistry, intestinal cells and microbial ecology. Levy proposes that chronic exposure to added iron may promote intestinal inflammation and increased permeability, although some of his broader claims remain hypotheses rather than established causes of specific diseases.
Should I take iron if I am tired?
Not automatically. Fatigue has many causes. Iron supplementation is most appropriate when laboratory testing demonstrates genuine iron deficiency and the reason for the deficiency has been considered.
Does Dr. Levy ever recommend iron supplementation?
Yes. Although Levy strongly criticizes unnecessary iron supplementation, he specifically acknowledges that genuine iron-deficiency anemia may require iron replacement. His concern is continued or unnecessary supplementation once adequate iron status has been restored.
Can hair analysis diagnose iron overload?
No. Hair analysis may provide useful information about broader mineral and toxic-metal patterns, but systemic iron overload should primarily be evaluated using ferritin, serum iron, TIBC or transferrin and transferrin saturation.
Iron Overload Testing & Related Resources
Measure iron status first, then evaluate the broader metabolic picture when elevated ferritin, oxidative stress, liver dysfunction, copper imbalance or methylation abnormalities are present.
This article summarizes Thomas E. Levy, MD, JD's Riordan Clinic lecture together with established principles of iron physiology, oxidative stress and laboratory interpretation. Some of Levy's broader claims concerning fortified iron, intestinal permeability, gluten sensitivity and chronic disease represent his mechanistic and clinical interpretation and should not be considered established causation. Iron deficiency and iron overload can both have important health consequences. Elevated ferritin alone does not establish iron overload, and significant abnormalities should be interpreted with complete iron studies, liver and inflammatory findings and appropriate medical evaluation.
Article references:
- "Neuroprotective effect of the natural iron chelator, phytic acid in a cell culture model of Parkinson's Disease" - Qi Xu, Anumantha G. Kanthasamy, and Manju B. Reddy
- "Role of Iron in Aging Related Diseases" - William J. Chen et al.
- "The Dark Side of Iron: The Relationship between Iron, Inflammation and Gut Microbiota in Selected Diseases Associated with Iron Deficiency Anaemia—A Narrative Review
Testing Metal Overload,;Iron (Ferritin) and Copper